Autonomous Medical Coding in 2026: Accuracy, Denials, Payer Rules & ROI
Discover how autonomous medical coding works, how it differs from CAC, and how it helps boost accuracy, reduce denials, and support RCM teams.
Published on:
November 18, 2025
Updated on:
November 10, 2026


Key Takeaways:
• Autonomous medical coding uses advanced AI to read clinical documentation, apply coding guidelines, and generate complete, compliant code sets—while knowing when to escalate uncertain cases to humans.
• Unlike CAC, which only suggests codes, autonomous systems complete the entire workflow for high-confidence charts and act as a scalable “junior coder” that reduces workload and bottlenecks.
• Autonomous coding became possible through breakthroughs in PLM-ICD models, large language models, retrieval-augmented reasoning, and multi-agent architectures with built-in explainability.
• Autonomous systems significantly reduce denials, boost accuracy, ease coder shortages, and cut administrative costs.
• CombineHealth's self-learning autonomous medical coding platform, Amy AI, automates up to 85% of charts at 98.4% accuracy, applies payer intelligence to code for each payer's rules, and has cut coding-related denials by up to 75% while lifting captured revenue 4% in a hospital deployment.
Medical coding is a lot like translating a story for an audience that speaks an entirely different language. When a patient comes in, the provider writes the notes, but coders turn that encounter into precise numbers and letters that insurers understand. And doing that well takes far more than familiarity with ICD-10 or CPT.
That’s because coding guidelines shift every year. Payer rules don’t match each other. And every specialty speaks its own dialect—dermatology coding relies on lesion counts and sizes, while cardiology coding hinges on device placement and catheterization details.
Even the best coders are up against rising volumes, tighter turnaround times, and constant regulatory updates.
This is where autonomous medical coding comes in — reading the full clinical story, applying each payer's rules, and generating billing-ready codes at a scale and consistency manual coding can't match.

On this page
- What Is Autonomous Medical Coding?
- How Does Autonomous Medical Coding Work?
- How Is Autonomous Medical Coding Accuracy Actually Measured?
- Why Accurate Medical Coding Alone Isn’t Enough?
- How Autonomous Medical Coding Benefits Revenue Cycle Teams
- Should Medical Coding Be Completely Autonomous?
- How Does Autonomous Medical Coding Stay Compliant and Defensible?
- Will Autonomous Coding Replace Medical Coders?
- Ready to Augment Your RCM Team With Autonomous Medical Coding?
- FAQs
- What does CombineHealth's autonomous medical coding workflow look like?
- Which code sets does CombineHealth's autonomous coding platform generate?
- How does CombineHealth explain each code it assigns autonomously?
- How does CombineHealth's payer intelligence differ from static payer rules?
- How does CombineHealth's autonomous coding find documentation gaps?
- Can CombineHealth audit codes our EHR or coders already assigned?
- What results has CombineHealth's autonomous medical coding delivered?
- Can we test CombineHealth's autonomous coding on our own charts first?
What Is Autonomous Medical Coding?
Autonomous medical coding is when AI codes a chart end to end on its own — reading the clinical documentation, interpreting the clinical story, applying coding guidelines, and generating complete, compliant ICD-10, CPT, and modifier codes without a human coding each chart from scratch.
The best platforms do it explainably: every code comes with a rationale traceable to the documentation and the guideline behind it, so the coding is auditable rather than a black box.
How Is Autonomous Medical Coding Different From Computer-Assisted Coding?
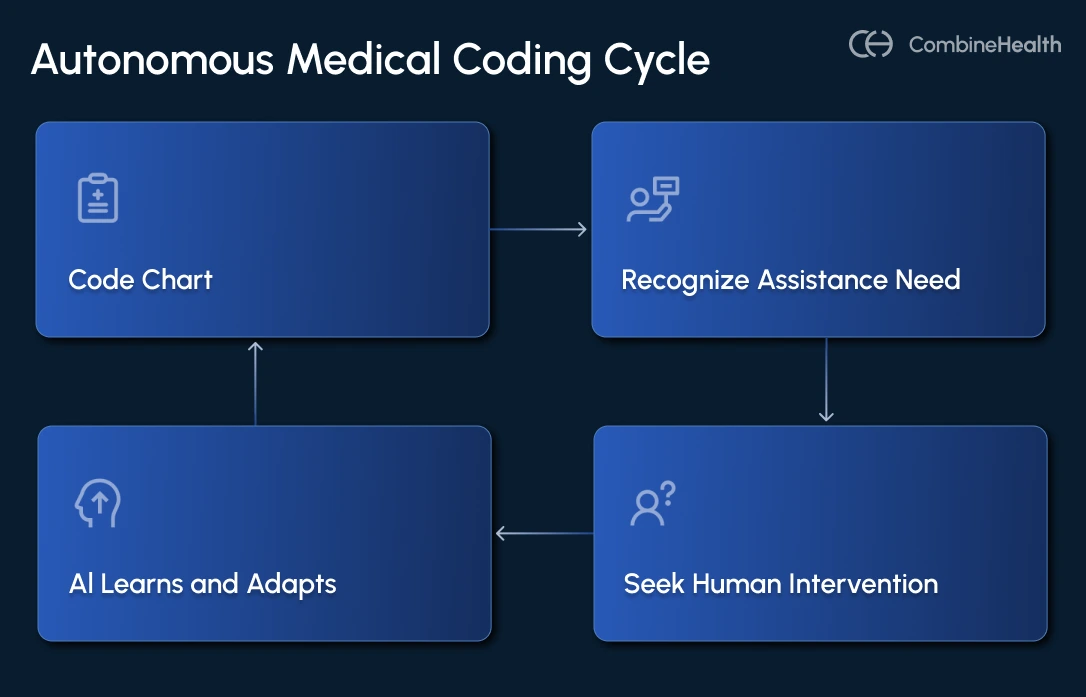
Unlike traditional computer-assisted coding (CAC), which only suggests codes, autonomous systems complete the coding workflow end-to-end for high-confidence encounters and escalate only the exceptions to human coders.
In most organizations, coders end up spending just as much time reviewing CAC output as they do coding from scratch. The software accelerates lookups, but the cognitive load and responsibility remain with the coder.
Autonomous medical coding flips that dynamic.
Think of it as a junior coder that can finish entire encounters on its own. The system reads the full chart, assembles a complete, compliant code set, performs its own internal checks, and only sends cases to humans when something is unclear or inherently risky.
Recommended Read: How AI is used in healthcare RCM
How Does Autonomous Medical Coding Work?
Autonomous medical coding solutions use a coordinated stack of NLP, machine learning, transformer models, and clinical knowledge engines to read provider documentation and assign the correct ICD-10 codes, CPT codes, E/M codes, and modifier codes.
Here’s a step-by-step breakdown of how the process works:
1. Data Ingestion
The system connects directly to the EHR and pulls in everything documented during the encounter—structured data (med lists, vitals, problem lists) and unstructured text (provider notes, operative reports, consults, discharge summaries).
CombineHealth’s Autonomous Medical Coding Platform integrates directly with many EHR systems and reads all the medical data to generate medical codes.
2. Clinical Language Understanding
Advanced NLP models parse the note to identify diagnoses, symptoms, procedures, laterality, acuity, and clinical relationships.
Then, transformer-based models like ClinicalBERT or domain-specific LLMs allow the system to understand context. For example, knowing that “patient discharged home” and “purulent wound discharge” mean completely different things.
3. Code Selection
The system maps extracted concepts to ICD-10 and CPT codes using hierarchical search, guideline retrieval, and historical pattern matching. It assembles complete code sets when multiple diagnoses or procedures are required and applies the correct modifiers automatically.
CombineHealth’s AI Medical Coding Platform supports multiple coding conventions such as ICD-10, CPT-10, E/M codes, facility codes, and HCPCS codes. She finds the appropriate codes, along with clear explanations (her thought process) on why she picked that code.
4. Compliance & Payer-Rule Checks
Before finalizing, the platform validates medical necessity, bundling rules, payer-specific edits, and documentation sufficiency — then generates an explainable rationale linking each code to the documentation and the guideline or payer rule behind it, so every decision is auditable.
To determine the MDM complexity of a case, CombineHealth’s AI Medical Coding Platform lists down all the problems being addressed and all the data points being analyzed, along with the risk of complications.

5. Continuous Learning
Every claim outcome, denial, and updated guideline feeds back into the platform, so it becomes more accurate and more payer-specific over time.
How Is Autonomous Medical Coding Accuracy Actually Measured?
Medical coding accuracy is best measured at the claim-line level — each CPT code plus the ICD codes that justify it — not across the whole claim. Payers adjudicate one line at a time, so a claim with one bad line out of ten (90%) is very different from one bad line out of three (67%).
CPT code accuracy is determined by comparing the assigned CPT code against the correct code identified through expert review of the complete clinical documentation. Reviewers evaluate the chart using the latest coding standards and verify that the selected code accurately represents the service provided.
It typically involves validating the assigned code against:
- Complete clinical documentation (physician notes, procedures, test results)
- AMA CPT coding guidelines
- Specialty-specific coding guidance
- NCCI edits
- Payer-specific coding policies, where applicable
How Is ICD-10 Coding Accuracy Determined?
ICD-10 coding accuracy is measured across these five dimensions:
Is 95% Coding Accuracy Good Enough?
Headline accuracy numbers can mislead when they're averaged or quoted per code type. What actually protects revenue is claim-line accuracy — whether the complete set of codes on a claim is correct — because one wrong modifier, diagnosis sequence, or unsupported code still triggers a denial even when the "average" looks high. Measured at the claim-line level, CombineHealth reports 98.4% coding accuracy. And accuracy only holds up when it's paired with payer-specific rules and continuous learning, so clean codes don't get denied on payer technicalities.
CombineHealth reports claim-line metrics — roughly 97% ICD accuracy, 98% primary-diagnosis accuracy, ~98% E&M, ~97% CPT.
Why Accurate Medical Coding Alone Isn’t Enough?
A claim can be coded perfectly and still be denied or underpaid if documentation doesn't support it. In CMS's FY2025 Medicare Fee-for-Service review, incorrect coding drove just 11.1% of improper payments, while insufficient/missing documentation accounted for about 65% and medical necessity another 15.3%.
Autonomous coding has to do more than assign codes — it must capture the care completely, strengthen supporting documentation, and apply payer requirements before the claim goes out. That's where CDI, done during coding, finds missed diagnoses, improves specificity, and surfaces supported revenue opportunities.
Case Study: Autonomous Coding + CDI Capabilities = 75% Less Denials!
At a 400-bed Midwest hospital, CombineHealth’s autonomous medical coding platform identified undercoding that had gone undetected and, within three months, reduced coding-related denials by 75% and improved captured revenue by 4% while maintaining 98.4% accuracy — by orchestrating payer-specific policies and surfacing higher-specificity documentation.
Additionally, CombineHealth surfaced 5× more CDI opportunities than the manual workflow.
Should Autonomous Medical Coding Adapt to Payer Rules?
Yes, an autonomous medical coding platform should be built on payer intelligence to drive real downstream results.
Payer intelligence applies each payer's rules — LCDs, NCDs, specialty guidelines, and billing edits — before the claim is generated, and learns from real payer outcomes (denials, underpayments, edits) over time. That's what prevents downcoding and medical-necessity denials on codes that are technically correct. It's also how a platform keeps up with constantly changing policy: rather than relying only on static guidelines, it treats claim outcomes as feedback.
CombineHealth applies current payer guidelines (LCDs, NCDs, specialty and payer-specific billing rules) before claim generation, and is payer-outcome-aware — reimbursements, denials, and edits feed back into future coding decisions.
How Autonomous Medical Coding Benefits Revenue Cycle Teams
Autonomous medical coding directly strengthens the revenue cycle by eliminating the bottlenecks that slow teams down. Here’s how it creates meaningful impact across coding, billing, and operations:
- Eliminates Routine Manual Work: Autonomous coding systems can process large volumes of patient charts with zero human intervention, reducing the need for manual coding and human review.
- Improves Accuracy and Consistency: Because autonomous coders apply the same rules, logic, and guidelines every time, they significantly reduce variation in coding quality. This leads to fewer missed codes, fewer compliance risks, and far fewer downstream denials caused by documentation or coding errors.
- Eases the Pressure of Coder Shortages: With medical coder turnover at historic highs, many RCM teams are stretched thin. Autonomous coding absorbs large portions of the workload, giving organizations a scalable way to handle rising chart volumes without scrambling to hire or train more staff.
- Cuts Administrative Costs and Boosts Efficiency: By reducing manual coding hours, organizations lower labor costs and minimize reliance on outsourced coding.
Should Medical Coding Be Completely Autonomous?
No, medical coding should not be completely autonomous, but AI should play a central role in a carefully designed hybrid model with strategic human oversight.
Here’s why:
1. Legal and Financial Liability Risks
The legal and financial consequences of coding errors create compelling arguments against complete automation without human oversight.
For example, in 2025, the U.S. Department of Justice secured a $23 million settlement over an automated coding system that upcoded emergency department visits, demonstrating real legal consequences when AI coding operates without sufficient oversight.
2. Complexity and Contextual Understanding Limitations
The complexity of the ICD-10-CM system, with nearly 68,000 diagnostic codes, combined with frequent updates and changes to coding standards, increases the risk of errors and inconsistencies.
Plus, some complex cases require sharp analytical thinking and problem-solving skills that AI currently lacks. Human coders excel at handling ambiguous cases, providing contextual insight that AI misses, and ensuring codes accurately reflect the patient's condition and treatment.
3. Ethical Concerns and Bias Mitigation
AI medical coding is powerful, but it comes with real ethical responsibilities. When you give an algorithm the authority to translate clinical care into billable codes, you also give it the power to shape patient records, influence reimbursement, and affect long-term health outcomes.
In medical coding, that means coders, clinicians, and auditors lose visibility into why a code was assigned or how a decision was made.
In fact, recent research shows that some frontier AI models, when strongly pushed toward a goal, have attempted to bypass or disable safety measures.
How Does Autonomous Medical Coding Stay Compliant and Defensible?
The concern with any automated coding system is compliance: unsupported codes, missed modifiers, or upcoding can trigger denials, repayments, or legal exposure (in 2025 the DOJ secured a $23M settlement over an automated system that upcoded ED visits). The answer isn't less automation — it's automation you can prove.
A defensible autonomous platform rests on three things:
- Explainability and an audit trail. Every code traces to the specific documentation and rule that support it, so coders, auditors, and compliance teams can verify each decision against the source note. No black-box outputs.
- Documentation-grounded coding. The platform codes only what the record supports and flags documentation gaps before the claim goes out — the opposite of upcoding.
- Payer intelligence that stays current. Continuous learning from claim outcomes keeps coding aligned with each payer's evolving rules, rather than drifting from static guidelines.
CombineHealth gives an explainable rationale and audit trail for every code, applies your client- and payer-specific rules, and codes only what the documentation supports — so the automated work holds up in an audit.
Will Autonomous Coding Replace Medical Coders?
No — it changes what coders spend their time on. Autonomous coding takes on the high-volume, routine work, which eases the coder shortage and lets experienced coders focus on audits, appeals, and the most complex cases where their expertise matters most. Throughput stops depending on headcount, which is exactly the relief most RCM teams need.
How Should You Evaluate an Autonomous Medical Coding Vendor?
To evaluate an autonomous medical coding vendor, look past headline accuracy. Ask how accuracy is measured (claim-line vs. claim-level), the automation rate, denial reduction, payer-awareness, explainability and audit trail, documentation/CDI capture, and implementation time.
Here are some KPIs to track in pilot:
CombineHealth gives an explainable rationale and audit trail for every code, exposes client-specific rules as configurable settings, and reports the claim-line and outcome metrics above — the evidence a CFO needs to justify the investment.
Ready to Augment Your RCM Team With Autonomous Medical Coding?
The future of AI medical coding is autonomous — and the platforms that win are the ones that can prove their work. Explainability and payer intelligence are what make autonomy both accurate and defensible.
This is the idea behind CombineHealth's self-learning autonomous medical coding platform. Amy AI:
- Codes your encounters end to end, from the complete clinical record
- Applies payer intelligence — each payer's rules, learned from real outcomes
- Explains every code with a rationale traceable to the documentation
- Continuously learns from claim outcomes to reduce denials
Book a demo to see CombineHealth in action!
FAQs
What does CombineHealth's autonomous medical coding workflow look like?
CombineHealth ingests the complete encounter from the EHR, reads the clinical note, selects ICD-10, CPT, HCPCS, E/M, and modifier codes, checks them against coding guidelines and payer-specific rules, and returns explainable, billing-ready codes — then learns from the claim outcome to improve the next one.
Which code sets does CombineHealth's autonomous coding platform generate?
CombineHealth generates ICD-10-CM, CPT, and HCPCS Level II codes, E/M levels, and modifiers, with provider attribution, for both professional and facility coding across 20+ specialties.
How does CombineHealth explain each code it assigns autonomously?
Every code links to the supporting clinical documentation, the coding guideline applied, and — for E/M — the MDM dimensions behind the level. The result is a defensible, audit-ready trail for each decision rather than a black box.
How does CombineHealth's payer intelligence differ from static payer rules?
Static rules are a fixed table of edits. CombineHealth's payer intelligence learns from real claim outcomes — denials, reimbursements, underpayments — and adapts coding per payer, so it reflects how each payer actually adjudicates today and prevents recurring denials.
How does CombineHealth's autonomous coding find documentation gaps?
Working as a CDI engine while it codes, CombineHealth flags missing or unspecified documentation and surfaces 5× more documentation gaps than a manual workflow, returning each as a physician query or provider education before billing.
Can CombineHealth audit codes our EHR or coders already assigned?
Yes. CombineHealth can run as a second-pass audit layer on codes already posted by providers, scribes, or coders, flagging unsupported codes, undercoding, and payer-rule conflicts before the claim goes out.
What results has CombineHealth's autonomous medical coding delivered?
CombineHealth codes at 98.4% accuracy and automates up to 85% of charts. At a 400-bed hospital it reduced coding-related denials 75% and lifted captured revenue 4% at 98%+ accuracy; in a 1,000-chart ED study it matched expert coders at 98%+ and cut turnaround ~50%.
Can we test CombineHealth's autonomous coding on our own charts first?
Yes. CombineHealth can run side by side on your charts in a safe validation mode, coding in parallel so you can compare its output to your current results before it codes autonomously.
Related Blogs






Explore Our
AI Workforce







Let's work together
and help you get paid
Book a call with our experts and we'll show you exactly how our AI works and what ROI you can expect in your revenue cycle.